AvDesk
Multisensory rehabilitation
with Physical AI

AvDesk is a Class I, non-invasive medical device for the assessment and treatment of visual, cognitive and sensorimotor deficits.
For adult and pediatric patients, in the clinic and at home.
Staff training and installation included.

WHERE AVDESK IS USED
In the clinic and at the patient's home
AvDesk consists of a panel that delivers visual and acoustic stimuli over 180°, the Physical AI system that guides the patient, and the platform on which the specialist works.
Two contexts of use, two solutions, but only one device.

At the patient's home
AvDesk Travel
The panel is flexible, rolls up, and can be placed on a standard desk. It weighs only 3.5 kg and travels in a carry-on trolley case.
The patient performs exercises independently, thanks to Physical AI, under the remote supervision of a specialist.
- Ready to use in 2 minutes
- Enables visual and cognitive exercises
- Can be used while seated
- Also suitable for wheelchairs
- Feedback via wireless button and voice response
- Home telerehabilitation.
Watch the video (3 minutes)
Installation in the clinic and a session at home

In the clinic
AvDesk Lift
The panel is rigid and the frame is for clinic use only. The motorized column moves the panel from 97 to 187 cm and orients it vertically, horizontally, or diagonally.
- Enables motor, visual and cognitive exercises
- Can be used standing or seated, for users with reduced mobility or in the recovery phase
- Also suitable for wheelchairs
- Feedback via joystick, voice response and ball.
- In combination with a stabilometric platform, it allows for the assessment and treatment of both visuospatial and postural/balance-related deficits.

Target audience
Who uses it and who is treated
AvDesk supports several kinds of professionals along the same care pathway, for adult and pediatric patients, who are able to cooperate and those who are not.
Who uses it
Rehabilitation
professionals
In hospitals, outpatient clinics, rehabilitation centers, nursing homes, private practices, and sports facilities.
Child neuro-psychomotor therapists (TNPEE)
Neurologists
Occupational therapists
Ophthalmologists
Orthoptists
Physiatrists
Physiotherapists
Speech-language pathologists
Strength and conditioning coaches
Who is treated
Adults, children
and geriatric patients
AvDesk can be used on patients who are able to cooperate and those who are not, adults and children suffering from:
Operating principles
Targeted treatment for
visual, cognitive and sensorimotor deficits
AvDesk applies multisensory stimulation to the treatment of visual, cognitive and sensorimotor deficits: an approach based on 40 years of neuroscientific research and over 20 years of international clinical studies.
Two independent lines of research, the rules of multisensory integration (Stein and Meredith, 1990) and adult neuroplasticity (Sale and Maffei, 2007), converge in a single device. The AvDesk hardware enforces coincidence, Physical AI verifies engagement, and the platform makes the result repeatable. The specialist decides the therapy.
Level 1 • the mechanism
Multisensory
integration
In 1986, Meredith and Stein demonstrated the existence of multisensory neurons in the superior colliculus capable of simultaneously receiving visual and auditory stimuli.
When these signals coincide in space and time, the response is not summed, it is amplified.
And it is amplified all the more as the individual stimuli are weaker, that is, precisely in the compromised field areas.
Spatial and temporal coincidence and inverse effectiveness are the two rules that Stein and Meredith formalized in 1990.
This mechanism orients gaze and attention toward the stimulus and reactivates visual exploration.

How AvDesk implements it
- Coupled bimodal stimulus
24 LEDs and 12 speakers integrated into the panel. Stimuli can be spatially and temporally coincident or dissociated, and delivered in sequence or in probabilistic order. - Multiple eccentricities
The panel covers 180°: the stimulus is placed where the deficit is located. - Maintained fixation
Physical AI guides and monitors the session and interrupts the sequence if the gaze leaves the expected range.
REFERENCES
- Meredith M.A., Stein B.E. (1986). Visual, auditory, and somatosensory convergence on cells in superior colliculus results in multisensory integration. Journal of Neurophysiology, 56(3), 640–662. DOI: 10.1152/jn.1986.56.3.640
- Stein, B E, and M A Meredith. Multisensory integration. Neural and behavioral solutions for dealing with stimuli from different sensory modalities. Annals of the New York Academy of Sciences vol. 608 (1990): 51-65; discussion 65-70. doi: 10.1111/j.1749-6632.1990.tb48891.x
Level 2 • consolidation
Neuroplasticity
and active engagement
In 2007, Sale and Maffei discovered in an experimental model that environmental enrichment restores visual acuity even in adulthood, beyond the critical period.
The brain reorganizes itself. Plasticity is driven by experience and repeated stimulation.
Sensory and cognitive enrichment promotes new synapses and the functional reorganization of cortical maps.
Change requires intensity, repetition, and participation: the brain does not change because it is stimulated, but because it is engaged.
The episode How the Brain Sees (SuperQuark, Rai 1), hosted by Piero Angela, explains brain plasticity in the rehabilitation of children and adults. AvDesk appears in the report.

How AvDesk implements it
The feedback accessories transform stimulation into an active and progressive task, and every patient response into measurable data.
REFERENCES
- Sale A., Berardi N., Maffei L. (2014). Environment and Brain Plasticity: Towards an Endogenous Pharmacotherapy. Physiological Reviews, 94(1), 189–234. DOI: 10.1152/physrev.00036.2012
- Sale A., Maya Vetencourt J.F., Medini P., Cenni M.C., Baroncelli L., De Pasquale R., Maffei L. (2007). Environmental enrichment in adulthood promotes amblyopia recovery through a reduction of intracortical inhibition. Nature Neuroscience, 10(6), 679–681. DOI: 10.1038/nn1899 · PMID: 17468749
Level 3 • VERIFICATION
What
is measured
Every session produces outcome parameters that are comparable over time.
- Reaction time
The most used index in literature, from the first studies on audio-visual stimulation in hemianopia (Bolognini et al., 2005) to RCTs on retinopathies and glaucoma. - Accuracy and false positives
Correctness at the first response and responses to absent stimuli: they distinguish improvement from anticipation. - Oculomotor parameters
Fixations, saccades, scanpaths, and head-gaze alignment. - Dose and adherence
Sessions delivered, actual duration, and completion.
Where it is applied
Visual deficits
Trains visual exploration and fixation stability.
In children with field defects from brain injury, multisensory training improves visual search, with protocols adapted to shorter sessions (Tinelli 2015, Tinelli 2017 and Tinelli et al. 2026 preprint).
In adults, stimulation reorients gaze and attention toward the compromised hemifield, while in nystagmus and maculopathy, it works on fixation and macular sensitivity.
PEER-REVIEWED RESEARCH
- Del Fabbro S., Jimenez B., Battaglia Parodi M. et al. (2025). Neurovisual rehabilitation of patients with geographic atrophy secondary to age-related macular degeneration with AvDesk system. European Journal of Ophthalmology. DOI: 10.1177/11206721251349039
- Antognetti D., Maggiani L., Gabbrielli E. et al. (2024). Neurovisual Training With Acoustic Feedback: An Innovative Approach for Nystagmus Rehabilitation. Archives of Rehabilitation Research and Clinical Translation, 6, art. 100371. DOI: 10.1016/j.arrct.2024.100371
- Zigiotto L., Damora A., Albini F. et al. (2021). Multisensory stimulation for the rehabilitation of unilateral spatial neglect. Neuropsychological Rehabilitation, 31, 1410–1443. DOI: 10.1080/09602011.2020.1779754
- Làdavas E., Tosatto L., Bertini C. (2020). Behavioural and functional changes in neglect after multisensory stimulation. Neuropsychological Rehabilitation, 32. DOI: 10.1080/09602011.2020.1786411
- Bolognini N., Fregni F., Casati C. et al. (2010). Brain polarization of parietal cortex augments training-induced improvement of visual exploratory and attentional skills. Brain Research, 1349, 76–89.
DOI: 10.1016/j.brainres.2010.06.053 - Bolognini N., Rasi F., Coccia M., Làdavas E. (2005). Visual search improvement in hemianopic patients after audio-visual stimulation. Brain, 128, 2830–2842. DOI: 10.1093/brain/awh656
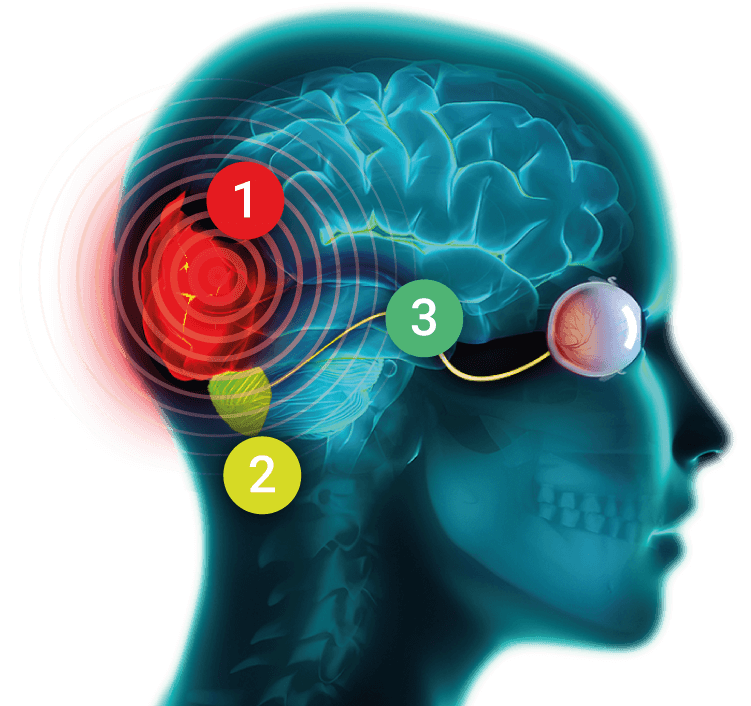
HOW it works
1. Visual cortex lesion
In the presence of visual cortex damage, visual processing for the corresponding area of the field is compromised.
2. The alternative pathway
Multisensory audio-visual stimulation activates the superior colliculus, a subcortical structure that receives visual and auditory afferents and integrates them when they coincide in space and time (Meredith and Stein, 1986).
3. The effect
Repeated activation promotes neuroplasticity (Sale, Berardi and Maffei, 2014) to support visual exploration in the compromised field.
Cognitive
and attentional deficits
Trains sustained attention, response times, and executive functions, with protocols that combine audio-visual stimuli with memory and choice tasks.
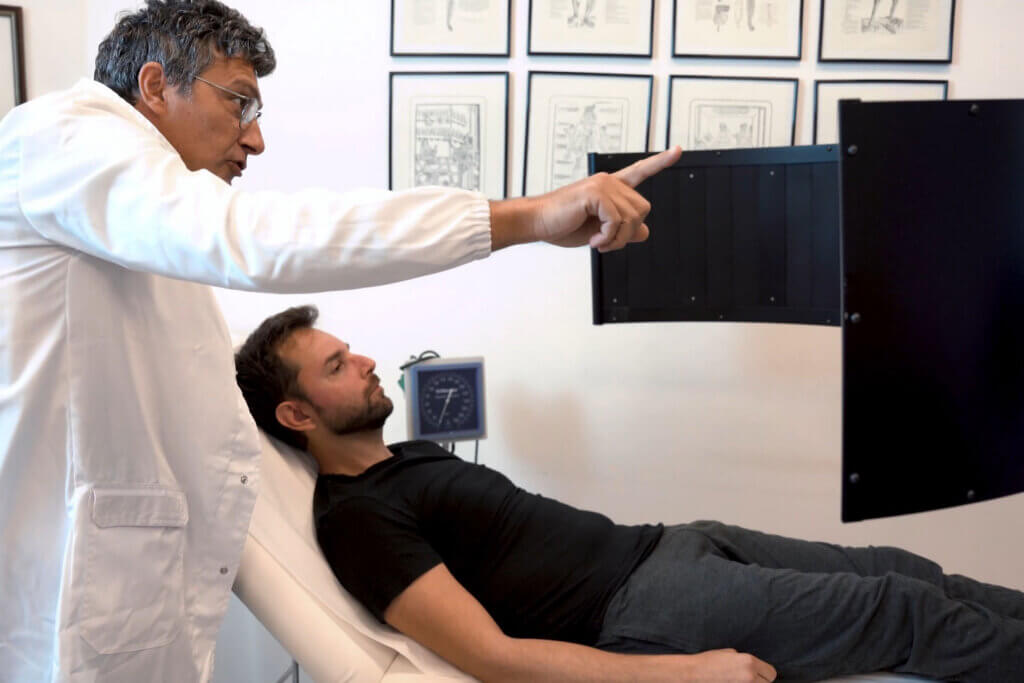
Application documented by internal clinical cases, not published in a peer-reviewed journal.
Sensorimotor deficits
Trains the integration between vision, proprioception, and the vestibular system: dual-task stimulation works on balance, postural stability, and movement safety.

The Centro Medico Giovanni XXIII in Treviso uses AvDesk Lift for visuo-perceptual and balance assessment in sports.
PEER-REVIEWED RESEARCH
- Calabrò R.S., Calderone A., Fiorente N. (2025). Neurosciences and Sports Rehabilitation in ACLR: A Narrative Review on Winning Alliance Strategies and Connecting the Dots. Journal of Functional Morphology and Kinesiology, 10(2), art. 119. DOI: 10.3390/jfmk10020119
- Ricupito R., Grooms D.R. (2025). Treating ACL Injury Associated Neuroplasticity: A Neurocognitive-Motor Rehabilitation Case Study. JOSPT Cases, 5(3), 120–126. DOI: 10.2519/josptcases.2025.0089
- Fu W., Yu X., Lai M. et al. (2024). Gamma oscillations induced by 40-Hz visual-auditory stimulation for the treatment of acute-phase limb motor rehabilitation after stroke: study protocol for a prospective randomized controlled trial. Trials, art. 284. DOI: 10.1186/s13063-024-08121-w
- Ricupito R., Grassi A., Zanuso M., Torneri P. (2025). The Influence of Cognitive Dual Tasking on the Outcomes of the Triple Hop Test Following Anterior Cruciate Ligament Reconstruction. International Journal of Sports Physical Therapy, 20(1). DOI: 10.26603/001c.127511
In-depth analysis
Rehabilitation, Prevention and Return to Sport
After ACL reconstruction, athletes shift toward visual control of the knee: proprioceptive input is impaired, and the motor task becomes a visual one. Dual-task multisensory training targets that shift.
The dedicated brochure draws on more than 30 international publications from Italy, the United States and China, including work by Kevin Wilk, Leonardo Cohen (NIH) and Ladan Shams (UCLA), with the outcome measures used and the treatment protocol with AvDesk Lift.

The operational path
A cycle that closes every day

The specialist defines protocol and duration on the Linari Medical Cloud platform

The patient performs
therapy in the clinic or
independently at home

AvDesk guides
and monitors
the patient and processes
daily graphs

The specialist adjusts
the therapeutic plan
based on progress
The stimuli
2 types of stimulus on a 180° panel
The specialist composes the session segment by segment.
They choose where to place the stimulus along the 180° arc and on the upper or lower row of LEDs, with which color and intensity, with which pitch and volume of sound, and whether the visual and acoustic stimuli are coincident in space and time or dissociated.
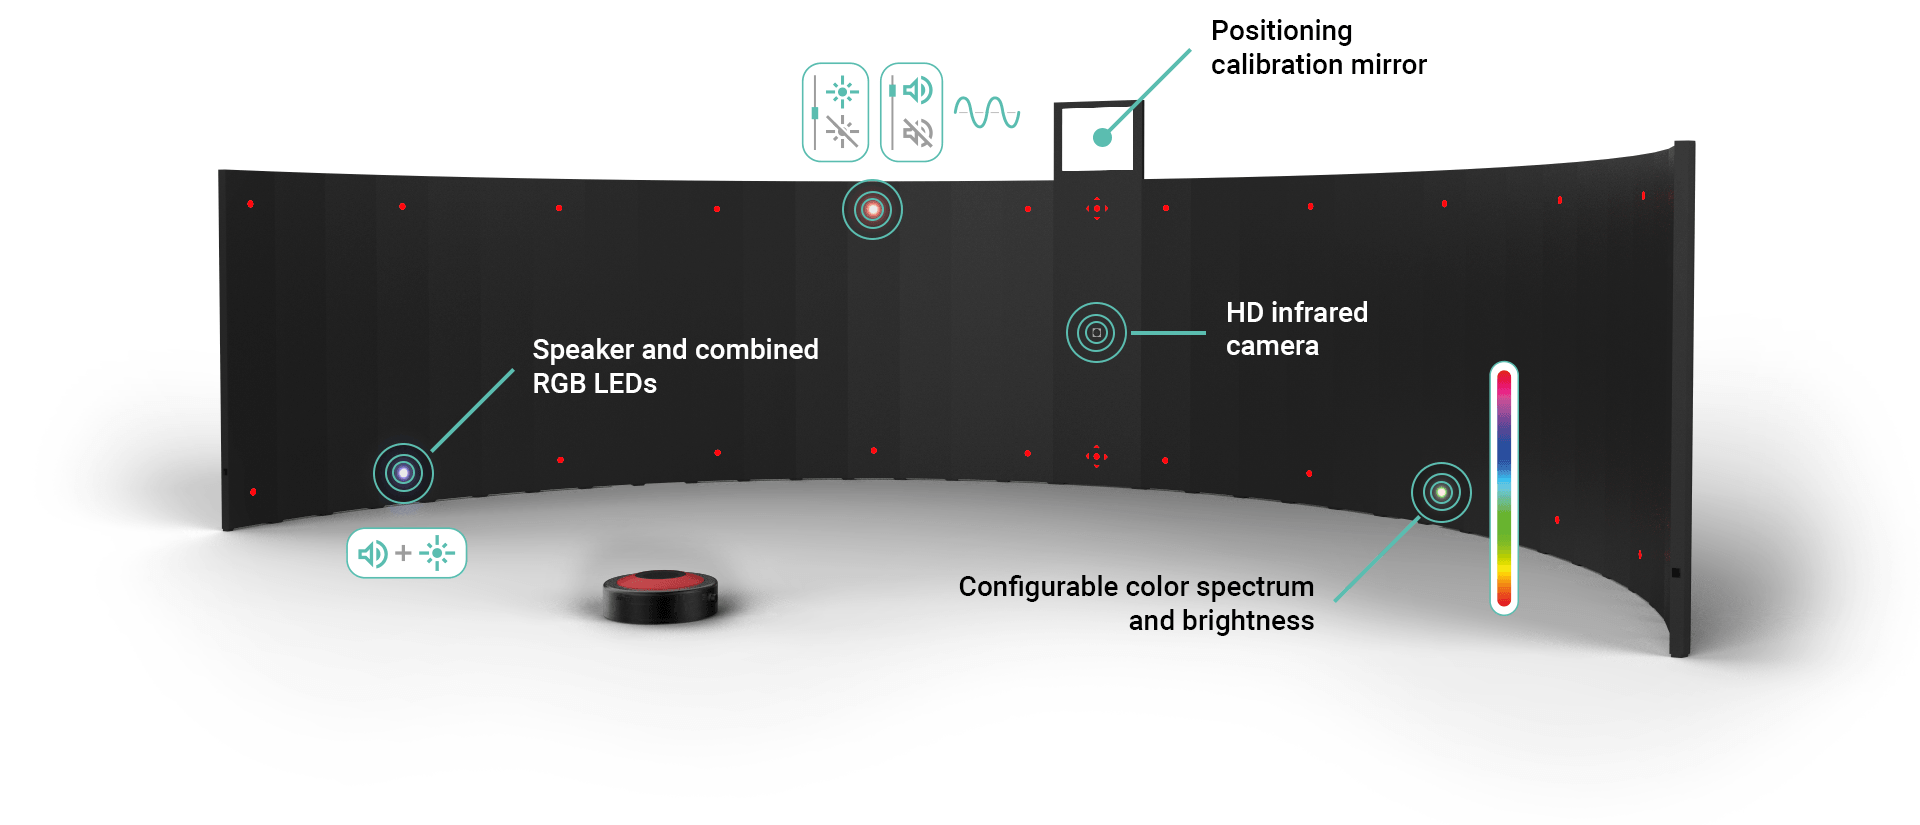
Light
12 segments with two rows of RGB LEDs, upper and lower, separately selectable. 16 million selectable colors, adjustable intensity.
The combination of segment and row allows for the isolation of a single quadrant of the visual field.
Sound
12 integrated speakers, one per segment. Adjustable volume and pitch, modulation from 13 to 100 Hz in band:
- beta: 13-30 Hz, associated with motor preparation
- gamma: 30-100 Hz, with documented protocols around 40 Hz for post-stroke functional rehabilitation.
How the patient responds
Feedback accessories
The response accessory is chosen based on the therapeutic goal and the person's abilities.

Wireless button
For home and clinic use:
- feedback with palm or fingers
- use while seated
- for right and left-handed users

Wired joystick
For precise control in standing sessions:
- held with the hand
- feedback with the thumb
- use while seated or standing
- for right and left-handed users

Ball
For motor-cognitive
recovery and enhancement:
- feedback with foot or hand
- use while standing or seated
- for right and left-handed users
- also for balance
Physical AI
What makes telemedicine possible
Execution fidelity, documented adherence to the plan, repeatable measures over time: this is what makes a session performed at home clinically reliable.
Physical AI is included in AvDesk and accompanies the patient throughout the journey, without requiring the constant presence of a specialist or therapist.

No images
are saved in the cloud
Linari Medical is certified ISO 27001:2022 for information security and ISO 13485:2016 for quality in medical devices.
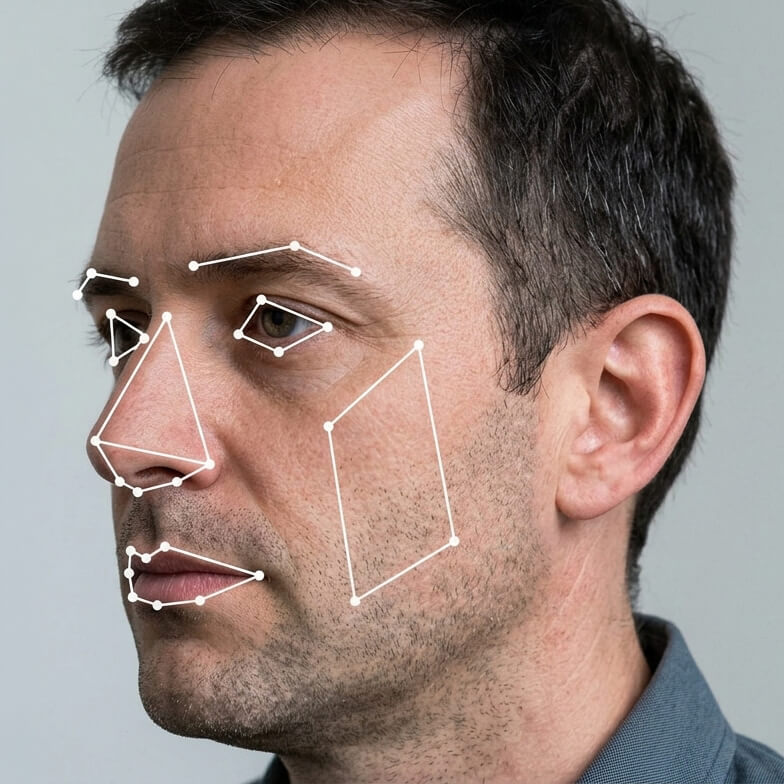
Monitors
AvDesk continuously compares the position of hundreds of facial points to derive orientation in space and gaze direction.
This is thanks to the integrated high-resolution camera in the device, with night vision and infrared illuminators.

Guides
When the patient moves out of the correct position, the four lighted arrows on the central AvDesk panel help them maintain the correct facial orientation.
If necessary, it pauses the rehabilitation session and suggests how to correct themselves.
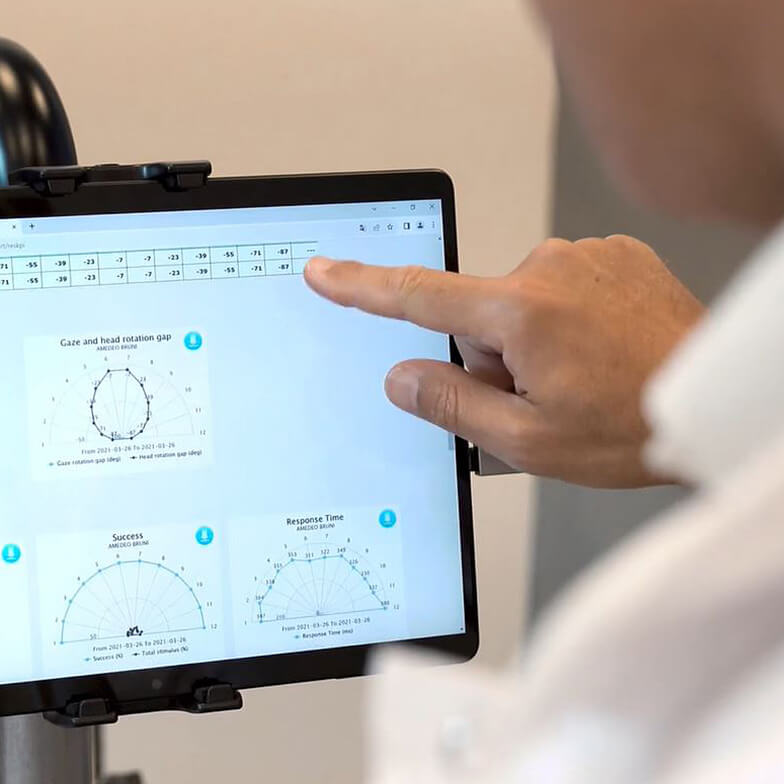
Processes
AvDesk records reaction times to the millisecond and gaze and head alignment for every stimulus.
The Linari Medical Cloud platform transforms data into graphs, where the specialist can read the treatment trend and adapt the therapeutic plan to the patient's evolution.
Gaze and head,
measured separately
The graph, processed by the Linari Medical Cloud platform, indicates whether the patient is compensating with head movement or if they are truly shifting their gaze, information that changes the protocol.
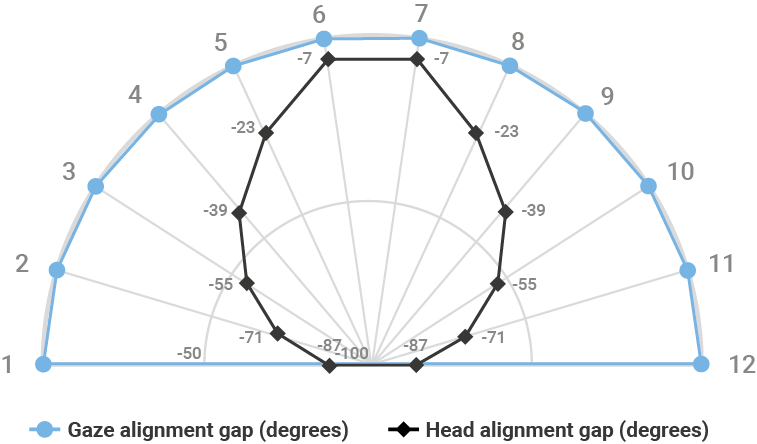
Gaze-only exercise, head fixed at the center
Zero, on the outer ring, means perfect alignment with the stimulus: gaze (●) sits there across all twelve segments, while the head (◆), held at the center, shows a gap that widens toward the edges.
In-depth analysis
Telemedicine
& Artificial Intelligence
Our book, published by Fabiano Editore, stems from the direct experience of doctors, engineers, and industry professionals, with the goal of offering concrete tools and practical insights for integrating telemedicine into daily practice.

(Currently available only in Italian)
AvDesk in the field
In use in clinical practice and research
AvDesk grew out of 10 years of clinical research with Fondazione Stella Maris in Pisa. Today it is used throughout Italy: in hospitals, IRCCS research institutes recognized by the Ministry of Health, rehabilitation centers, nursing homes and private practices.
1,000 patients treated
50 centers and specialists
3 IRCCS with published studies
20+ years of peer-reviewed literature
Clinical studies with AvDesk have been carried out at Istituto Auxologico Italiano, Fondazione Stella Maris, Fondazione Don Carlo Gnocchi and Azienda Ospedaliero-Universitaria Pisana (Pisa University Hospital).
In community and patient-support settings, AvDesk is used in collaboration with Fondazione Chiossone in Genoa and Istituto dei Ciechi Francesco Cavazza (institute for the blind and partially sighted) in Bologna.
Findings have been published in Brain, Neuropsychologia, Neuropsychological Rehabilitation, Multisensory Research, the European Journal of Ophthalmology and the Journal of NeuroEngineering and Rehabilitation.

Results
What the data show
CASE STUDY
Cleared to drive
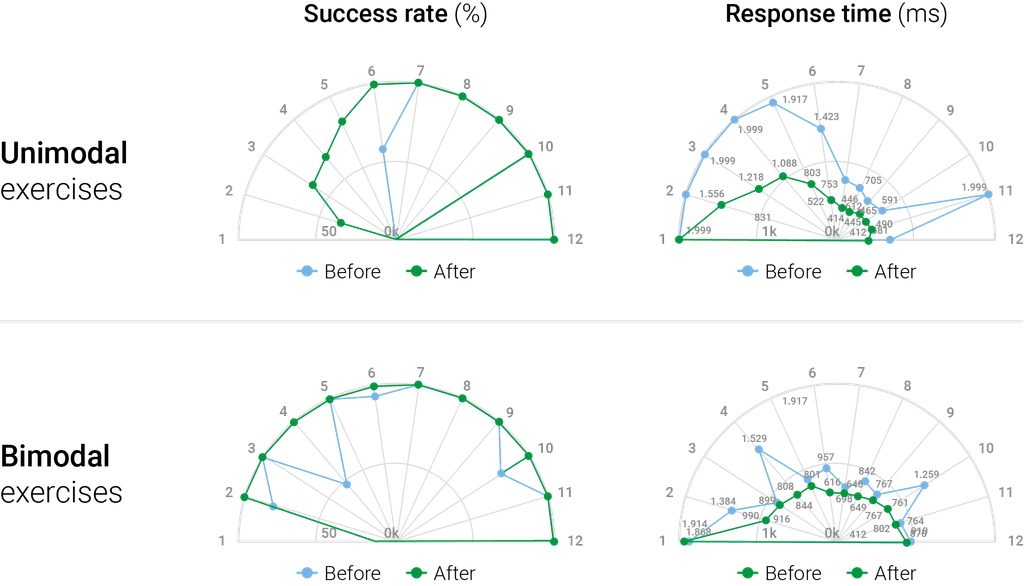
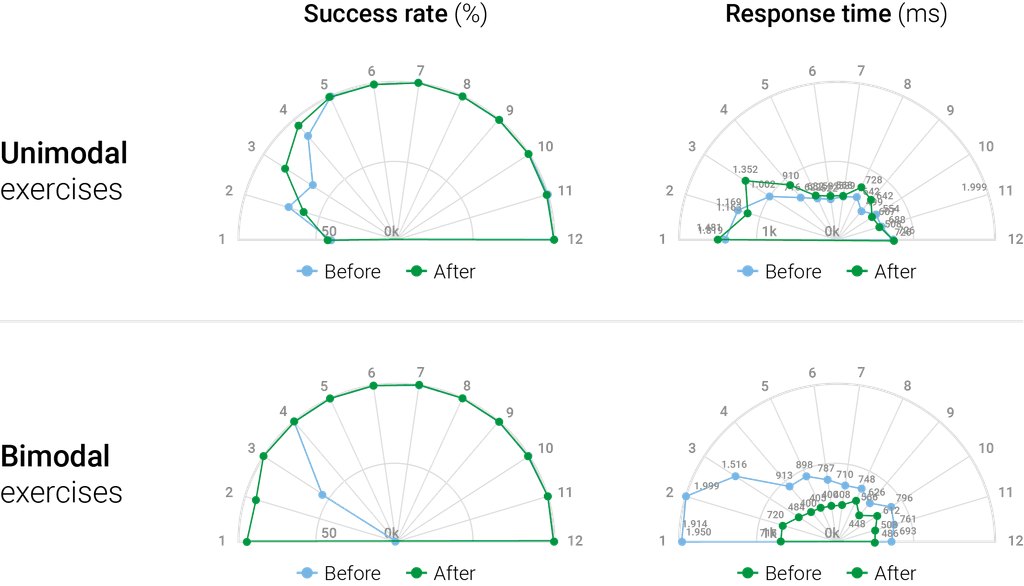
At the IRCCS Don Carlo Gnocchi in Florence, two men aged 59 and 52 with hemianopia underwent one month of rehabilitation with AvDesk, two sessions per week. Pre- and post-visual tests showed an improvement in eye movements and the appearance of responses to stimuli previously not perceived in the blind hemifield.
Both patients were cleared to drive again.
The graphs below, produced by the Linari Medical Cloud platform, compare patient performance recorded in both unimodal (light only) and bimodal (light and sound) exercises. The blue line represents performance at the start of treatment and the green line represents performance at the end of the rehabilitation path.
Subject 1 (59-year-old man)
Subject 2 (52-year-old man)
Internal case study, IRCCS Don Carlo Gnocchi, Florence, 2025. Not published in a peer-reviewed journal.
Neuroimaging
Functional magnetic resonance imaging has documented, in patients with hemianopia treated with AvDesk for 2 weeks, cortical activation in response to stimulation (in red and purple) of a quadrant of the visual field that was previously not represented.
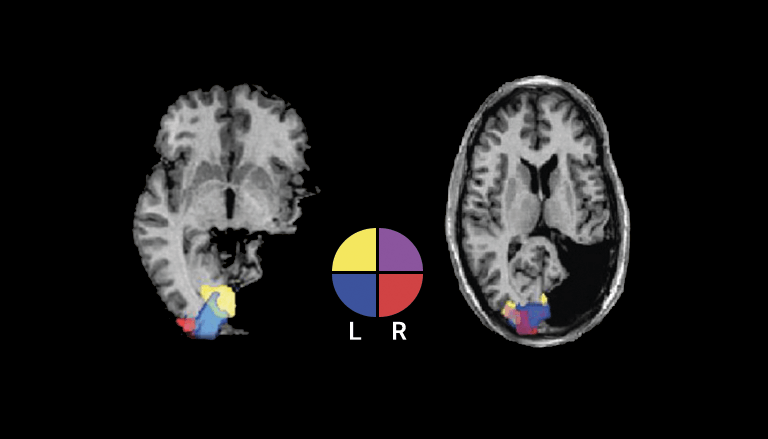
Pre-therapy
POST-therapy
Tinelli, Francesca et al. Blindsight in children with congenital and acquired cerebral lesions. Cortex; a journal devoted to the study of the nervous system and behavior vol. 49,6 (2013): 1636-47.
DOI: 10.1016/j.cortex.2012.07.005
Reading test
In a study of 12 patients with chronic visual field deficits and 12 healthy controls, the first two weeks of training with visual stimuli only did not change reading speed.
The subsequent two weeks, treated with AvDesk but with audio-visual stimuli (4 hours a day), produced a 275% increase in reading speed (from 1.6 to 6 syllables per second). After one year, a 113% increase remains.
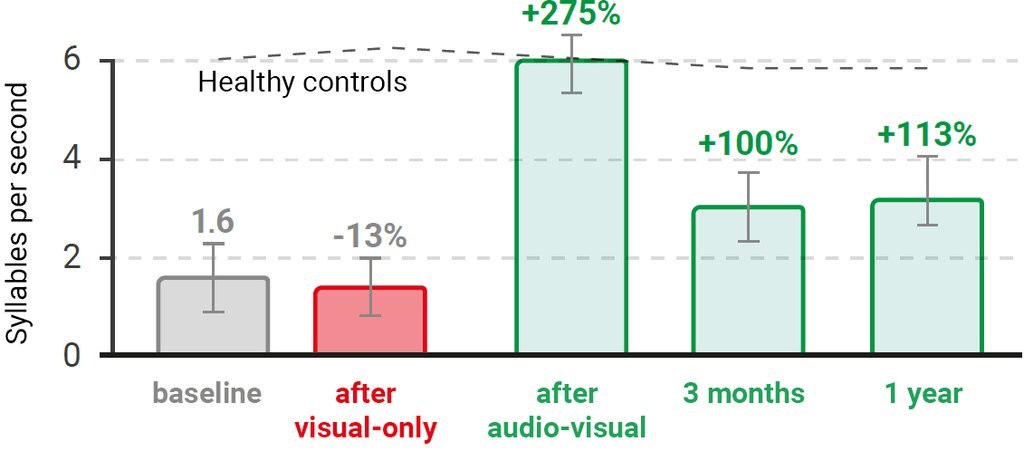
Passamonti C., Bertini C., Làdavas E. (2009). Audio-visual stimulation improves oculo-motor patterns in patients with hemianopia. Neuropsychologia, 47, 546–555. DOI: 10.1016/j.neuropsychologia.2008.10.008
Telerehabilitation
Home training improves visual search accuracy and speed, reading, mood, and disability in activities of daily living, with improvements that persist for up to 6 months after the end of training.
The clinical study authors conclude that telerehabilitation, acting as functional compensation, produces effects comparable to those in person.
Telerehabilitation represents an option to continue therapy in the chronic phase in an independent, intensive, and active way at home, under the remote supervision of a specialist.
Bolognini, N., Diana, L., Rossetti, A. et al. Telerehabilitation for visual field defects with a multisensory training: a feasibility study. J NeuroEngineering Rehabil 22, 34 (2025). DOI: 10.1186/s12984-025-01573-4
LINARI MEDICAL CLOUD
The software that governs therapy
and the facility that delivers it
Linari Medical Cloud is our clinical operating platform: a cloud solution for managing medical centers, hospitals and outpatient clinics.
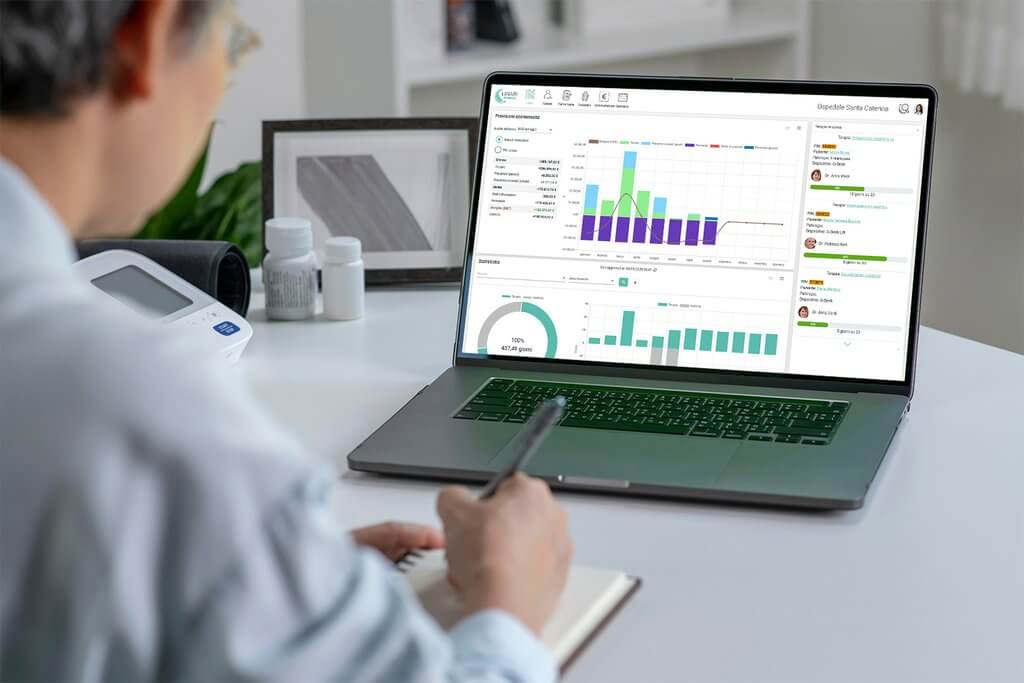
The platform is intended exclusively for medical personnel and can also be used with devices already present in your healthcare facility.
Clinical Area
- Patient registry and records
- Personalized therapies and prescriptions
- Real-time results, graphs, and KPIs
- Compliant storage of clinical reports
- Private chats with staff and patients
Management Area
- Therapy quotes
- Staff performance
- Financial forecasts
- Device usage
Logistics Area
- Schedule and session booking
- Device booking and rental
- Home shipping and returns
- 24-hour support and replacement
Try AvDesk
in your facility
for one month
With your patients, in your own space,
with your staff trained by us.
Are you a patient or a family member?
Find a center or a specialist
Content intended for healthcare professionals
Frequently Asked Questions
If you have further questions, please contact us.
What is AvDesk?
AvDesk is a Class I medical device produced by Linari Medical for neuro-visual and cognitive assessment and rehabilitation in telemedicine. It combines multisensory audio-visual stimulation, artificial intelligence, and the Linari Medical Cloud platform, allowing for use at the patient's home under the remote supervision of specialized doctors and therapists.
Who is AvDesk for?
AvDesk is indicated for adult and pediatric patients, who are able to cooperate and those who are not, with neuro-visual and cognitive deficits including hemianopia, neglect, nystagmus, geographic atrophy, Alzheimer's disease, attention disorders, and post-stroke recovery. It is also used in the cognitive enhancement of athletes, pilots, professional drivers, and armed forces requiring high visuo-attentional performance.
What pathologies can AvDesk treat?
AvDesk supports the clinical assessment and treatment of hemianopia, quadrantanopia, unilateral spatial neglect (neglect), nystagmus, geographic atrophy (advanced form of age-related macular degeneration), cognitive decline, Alzheimer's disease, and post-stroke. In pediatric age, it is used for SEN, SLD, and congenital visual field defects.
How does AvDesk work?
The device delivers spatially and temporally coordinated visual and sound stimuli through a curved stimulation panel. The patient responds by pressing a wireless button or, if patient cannot press a button, via Gaze and Head Tracking. An IR camera and an artificial intelligence system monitor attention and posture in real time. Reaction time, measured in milliseconds, quantifies improvements.
What is the scientific basis for AvDesk?
The method is based on two consolidated neuroscientific foundations: multisensory integration described by Barry Stein and Alex Meredith (superior colliculus neurons that amplify responses to visual and sound stimuli coincident in space and time) and adult brain plasticity studied by Lamberto Maffei (synaptic reorganization driven by experience, repetition, and active patient involvement).
What is the therapeutic protocol with AvDesk?
Therapy requires sessions of about one non-continuous hour per day for twenty days. The protocol is defined daily by the specialist doctor remotely via Linari Medical Cloud, based on the pathology and progress detected. Significant improvements in reaction times are typically observed after just two weeks of treatment.
Does AvDesk have contraindications or side effects?
AvDesk is a Class I non-invasive medical device: it delivers light and sound stimuli and does not administer drugs or electrical stimulation.
Observed side effects are transient and related to the attentional effort required by the session: fatigue from prolonged concentration, eye burning, or dryness. In documented use, no clinical worsening has been found.
Two precautions. In the presence of epilepsy, a preliminary clinical evaluation is necessary. In pediatric age, or in case of severe deficits, the session should be carried out with the assistance of a professional or a caregiver.
Complete indications, warnings, and methods of use are reported in the User Manual.
What is the difference between AvDesk Travel and AvDesk Lift?
AvDesk Travel is the portable version: rollable carbon fiber panel, mini trolley with aircraft cabin dimensions, designed for home rehabilitation. AvDesk Lift is equipped with a motorized column with remote control to position the device vertically, horizontally, or diagonally: it is designed for clinics, outpatient clinics, nursing homes, gyms, and professional rehabilitation centers.
Can AvDesk be used without the physical presence of a doctor?
Yes. Telemedicine is the primary usage paradigm. The patient performs sessions at home while the doctor and therapist supervise remotely via Linari Medical Cloud. The integrated Physical AI system (IR camera, Gaze and Head Tracking, and luminous guide arrows) automatically maintains the attentional level and correct posture, ensuring therapeutic adherence even in the absence of an on-site operator.
What role does Physical AI play in AvDesk?
Physical AI tracks the patient's gaze, head position, and attention in real time, checking that each trial is performed correctly. It also allows the device to be used with patients who cannot press a button (disorders of consciousness, severe motor impairment, young children) because gaze tracking replaces the manual response. The data it records is what the specialist uses to adjust the plan.
Is AvDesk a certified medical device?
Yes. AvDesk is classified as a Class I medical device and is covered by an international patent valid in the European Union, Switzerland, the United States, and Japan. It is produced by Linari Medical srl, a company based in Pisa, and developed through a multi-year collaboration with the IRCCS Fondazione Stella Maris in Pisa, an international benchmark in child neuropsychiatry.
Can AvDesk be rented or must it be purchased?
Linari Medical offers both options. The operating lease allows access to the device without purchase costs, with a period that can be extended as needed, technical assistance included, full-risk insurance, replacement or repair within 24 hours, and tax deductibility. Linari Medical directly manages shipments to patients and returns.
Who makes AvDesk, and for how long?
AvDesk is designed and produced by Linari Medical srl (Via Gaetano Malasoma 26, 56121 Pisa, Italy). The project was born in 2010 from the multi-year work of Linari Holding in collaboration with the IRCCS Fondazione Stella Maris in Pisa, with over twenty years of research behind it on neuro-visual deficits and neuroplasticity.